

Baby Drinks Bottle Too Fast? How Long a Feed Should Take (+ Fix)
By Simple Baby Tracker Editorial TeamBaby Care
Baby finished the bottle in 5 minutes? Learn how long a feed should take, signs the nipple flow is too fast vs. baby still hungry, and paced bottle feeding fixes.

Key Takeaways
- A paced bottle feed should take about 15–20 minutes — roughly as long as a breastfeed. Five minutes usually means the flow is doing the work, not your baby.
- A 5-minute finish does not automatically mean “make a bigger bottle.” Check flow-too-fast signs first, hunger cues second.
- Gulping, choking, coughing, hard swallowing, milk leaking, and increased drooling or spit-up point to flow too fast — slow the nipple down, don’t size up.
- Rooting, hands to mouth, and fussing after a pause point to genuine hunger — then offer more, about an ounce at a time.
- There is no need to move up a nipple level by age. Many babies stay on the same slow-flow nipple the whole bottle-feeding period.
The short answer
Your baby finished the bottle in 5 minutes. Two explanations compete: the nipple flow is too fast, or your baby genuinely needs more milk. Bet on flow first. A paced bottle feed should take about 15–20 minutes, mimicking a breastfeed 1. When a full bottle disappears in 5, gravity and a fast nipple usually did the feeding — your baby just swallowed fast enough to keep up.
That matters because a baby who “finishes fast” often looks hungry afterward even when they had enough: the feed ended before fullness signals caught up, or they swallowed air along the way and feel unsettled rather than satisfied. Slow the feed down before you size the bottle up. If the slow feed still ends with hunger cues, then offer more.
How long should a bottle feed take?
The benchmark comes from La Leche League: hold the bottle horizontal so the baby has to suck actively, and the feed should take about 15–20 minutes, mimicking time at the breast 1. Other lactation sources describe the same paced-feed window at roughly 10–20 minutes 2. The exact number matters less than the principle: a bottle feed should look unhurried, with pauses, not like water draining from a jug.
Use this as your ruler:
| Feed duration | What it usually means |
|---|---|
| Under 10 minutes, full bottle gone | Flow too fast until proven otherwise |
| 10–20 minutes with pauses | Healthy paced feed |
| Over 30 minutes, baby working hard, frustrated or falling asleep mid-feed | Flow may be too slow, or baby is tired rather than hungry |
One corridor deserves care: a feed that drags past 30 minutes with fast sucking, few swallows, a collapsing nipple, or fussiness points to flow too slow — the mirror image, and the case for sizing up 3. Everything in this article is about the opposite corridor, so don’t apply the “slow down” advice to a baby who is already struggling to get milk out.
Newborn feeds run long and variable at first, then settle into the paced rhythm as your baby’s suck-swallow-breathe coordination matures. For the amounts behind the clock — ounces per feed by age — our formula feeding chart by age and newborn feeding guide have the tables.

Possibility 1: the flow is too fast (most common)
When the nipple gives milk faster than your baby can comfortably swallow, the baby’s only options are gulp, choke, leak, or quit. A 5-minute empty bottle with any of the signs below is a flow problem wearing a hunger costume.
Watch for these during the feed — they are the standard “too fast” signs used by children’s hospitals and nipple-flow guidelines 34:
- Gulping — rapid audible swallowing, one gulp per suck with no pause pattern
- Choking, coughing, or hard swallowing — baby struggles to coordinate sucking, swallowing, and breathing against the flow 5
- Milk leaking from the corners of the mouth — more arriving than baby can manage
- Wide eyes, pulling off, or bottle refusal mid-feed — overwhelmed, not uninterested
- Increased drooling or spit-up after very fast feeds — overfilling plus swallowed air
- Falling asleep at the very start — shutting down rather than settling in 4
- Short feed followed by fussiness within minutes — the classic false-hunger signal: stomach filled too fast for satiety cues to register
Two extra risk flags come from the breastfeeding literature but apply to any fast flow: an overwhelmed baby may clamp down, refuse the breast later, or develop a flow preference for the faster source 2. If you combination-feed, this is the reason lactation guidance holds combination-fed babies on slow-flow nipples — to keep the bottle from outrunning the breast 3.
The age-trap: don’t size up by the calendar
Almost every nipple brand prints an age range on the packaging. Ignore it as a schedule. Nationwide Children’s Hospital is explicit: if your baby is healthy, growing, and enjoys the bottle, keep following your baby’s pace — a baby may stay on the same level nipple the whole time they take bottles, and that is fine 3. Move up only on signs (feeds getting much longer, fast sucking with few swallows, nipple collapsing, fussiness while working), never on birthdays.
Worn-out nipples deserve a check too: thinning, stickiness, color change, or tears all effectively enlarge the hole and speed up flow. Test by pulling the nipple tip firmly — it should snap back to shape; if not, replace it 3.
Possibility 2: your baby genuinely needs more milk
Sometimes the answer really is “more milk” — growth spurts, a bigger baby, or a bottle that was simply under-mixed for today’s appetite. The trick is reading hunger after a properly paced feed, not after a 5-minute chug.
Offer a paced feed first. Then, after a burp break, look for true hunger cues. The CDC lists these hunger signs for babies under 5 months: hands to mouth, turning toward the bottle, puckering or lip-smacking, and clenched hands — noting that crying is a late sign, so earlier cues are the ones to watch 6:
- Rooting — turning toward touch on the cheek, or toward the bottle itself 6
- Hands to mouth, lip-smacking, or sucking motions that persist after burping 6
- Fussing that starts when the bottle ends and settles the moment sucking resumes
- Waking and demanding again unusually soon with a strong, organized suck — not the restless squirm of gas
Contrast those with fullness cues: closing the mouth, turning away from the bottle, and relaxing the hands 6 — plus the older-baby versions: sealing lips, pushing the nipple out with the tongue, relaxed open hands, falling into a contented sleep. A baby showing fullness cues after a fast feed had enough milk delivered too quickly — the fix is pacing, not ounces. A baby showing hunger cues after a slow 15-minute feed with a calm suck probably wants another ounce or two; offer about an ounce at a time and re-check.
For the intake side of this judgment — how many ounces per day at your baby’s weight and age — anchor on the formula feeding chart. And if night feeds are part of the “still hungry” pattern, how long to track newborn feedings covers when frequent feeding is developmental and when to ask about it.
| Signal | More likely flow too fast | More likely still hungry |
|---|---|---|
| Feed duration | Under 10 min, bottle “disappears” | 15–20 min paced, baby still cues |
| During feed | Gulping, coughing, leaking, pulling off | Steady rhythmic suck-swallow, calm |
| Right after | Fuss + spit-up, or drowsy shutdown | Rooting, hands to mouth, settles only when sucking resumes |
| Fix to try first | Slower nipple + paced technique | Offer ~1 oz more, re-check cues |
What to do: the paced bottle feeding fix
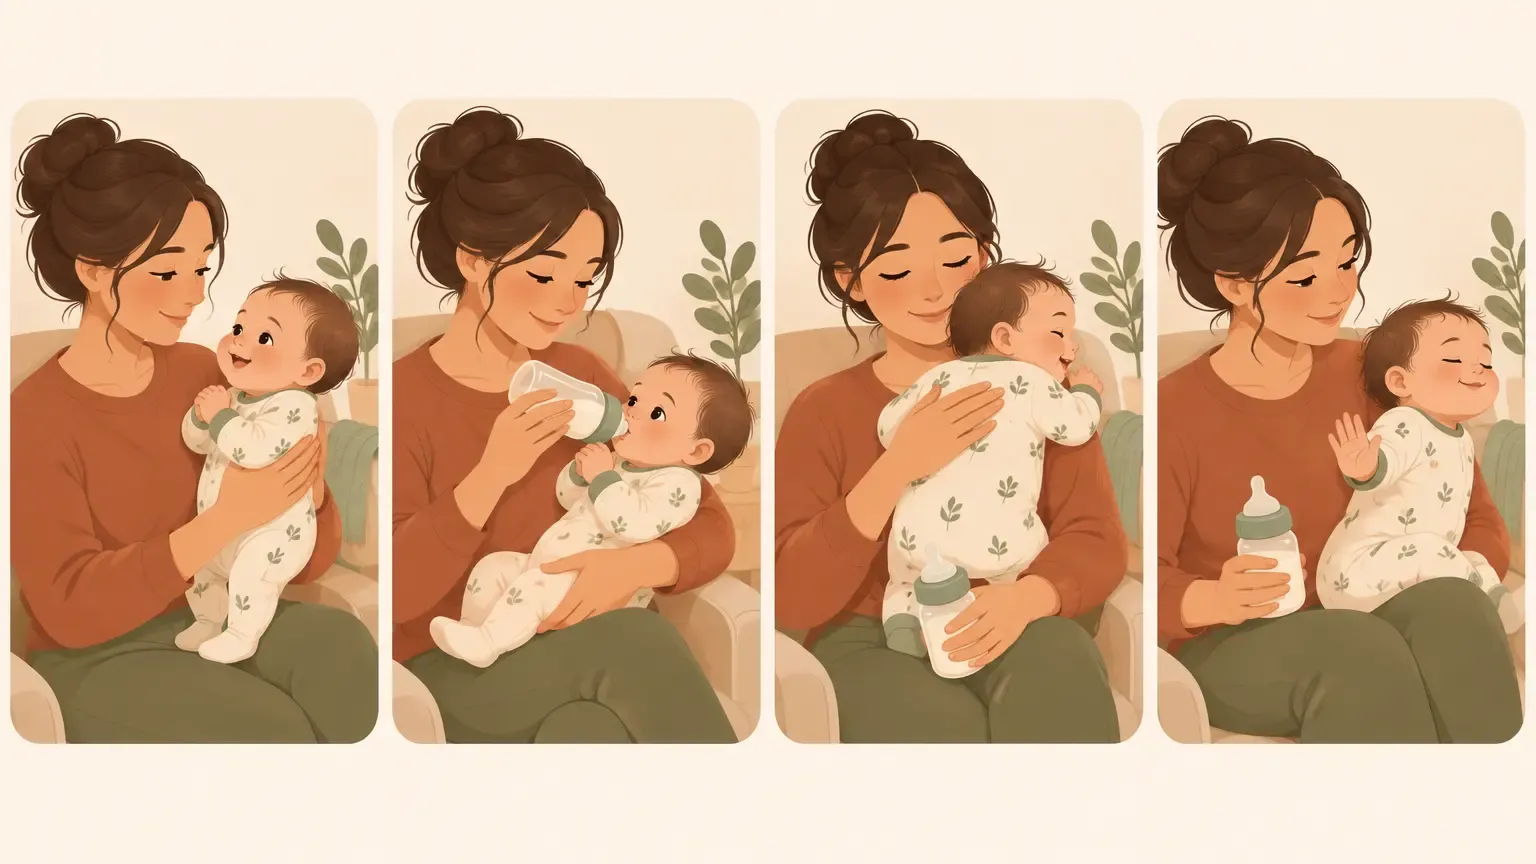
Paced feeding makes the bottle behave like the breast: baby works for the milk, pauses happen, and the feed lands in the 15–20 minute window 1. Steps, in order:
- Hold your baby upright, head and neck supported — never flat on their back. Semi-upright is the safe feeding posture.
- Hold the bottle horizontal, nipple just filled at the tip — not angled down pouring milk in. Baby should have to suck actively to draw milk 1. The CDC phrases the same rule as: angle the bottle so milk comes only when the baby sucks 7.
- Start with the slowest-flow nipple you own (often labelled “slow,” “newborn,” or level 0/1), regardless of your baby’s age. Combination-fed babies especially stay slow 3.
- Pause every few minutes: lower the bottle (keep the nipple in the mouth) or remove it for a burp break. Watch for the baby re-latching with interest versus turning away. Let breaks happen whenever the baby seems to want them 7.
- Let the baby set the length. A feed with pauses that stretches toward 15–20 minutes is the goal — do not jiggle, re-offer, or compress it back to 5.
- End on baby’s cues, not the ounce marks. Lips sealed, head turned, tongue pushing out: done, even with milk left 7. The CDC is blunt here: do not force the baby to finish the bottle — it leads to eating more than needed — and never prop the bottle and walk away (choking, ear infection, and tooth-decay risk, plus overfeeding) 7. Still rooting after a burp break: offer ~1 oz more.
If fast-feed symptoms persist on the slowest nipple, try a different bottle system before assuming anything about your baby — flow rates are not standardized across brands, and one company’s “slow” can run faster than another’s “medium” 3. Lab testing of 26 common nipple types put numbers on this: nipples all labelled “Slow,” “Newborn,” or “0–3 months” ranged from 1.68 mL/min (Avent Natural Newborn) to 15.12 mL/min (NUK slow flow) — a 9-fold spread behind the same words — and even two Avent “Newborn Flow” nipples differed significantly (8.19 vs. 1.68 mL/min). The authors’ conclusion: the label is not a reliable guide to actual flow 8. UNICEF’s Baby Friendly guidance adds the responsive-feeding frame for all of this: feed on early hunger cues (head turning, mouth opening, sucking fingers — crying is the last sign), not on ounce targets 9.
When to size up vs. size down
This is the decision parents get backwards most often: a baby finishing fast looks like they “graduated” to the next nipple level. They usually need the opposite.
Size down (or stay slow) when: gulping, choking, coughing, hard swallowing, leaking, increased drooling, refusal, or sub-10-minute finishes 34. Also size down when a brand change quietly sped things up.
Size up when: feeds stretch much longer than before, sucking is fast with few swallows, the nipple collapses, or the baby fusses while working hard for little return 3. Note these are effort signs, not speed signs — a content fast drinker is not asking for a faster nipple.
Stay put when: baby is healthy, growing, and finishes calmly in roughly the paced window. No calendar date overrules that 3.
When to call the pediatrician
Fast feeding is usually a technique problem, but a few patterns deserve professional eyes:
- Choking or coughing at most feeds despite the slowest nipple and paced technique — possible swallowing-coordination issue 5
- Frequent vomiting (not small spit-ups), especially forceful or projectile vomiting
- Poor weight gain, dropping centiles, or persistently fewer wet diapers
- Bottle refusal lasting multiple feeds, or falling asleep at the start of every feed 4
- Breathing difficulty during feeds: fast or labored breathing, color change, apnoea-like pauses
Log what you see before the visit: feed start/end times, ounces offered vs. taken, which signs appeared and when. A written feed log turns “she drinks too fast” into a pattern the pediatrician can act on — our tracking without data anxiety guide keeps that log to seconds per feed.
Frequently asked questions
My baby drains 4 oz in 5 minutes and cries. More milk?
Probably not yet. A 5-minute drain with crying right after fits flow-too-fast plus swallowed air: burp first, then offer a slow paced re-feed or ~1 oz and watch the cues. Crying that settles only with rhythmic sucking points to hunger; crying with arching, spit-up, or restless squirming points to overfilling and air.
Will a fast flow ruin breastfeeding?
It can create a flow preference: if the bottle always runs faster than the breast, some babies get frustrated at the breast and refuse it 2. The protection is slow-flow nipples plus paced technique for every bottle, so both sources feel like similar work.
What nipple level should my baby’s age use?
No universal level exists — brands don’t standardize flow rates, and hospitals advise following your baby’s signs rather than package ages 3. Start slow, move up only on effort signs (longer feeds, collapsing nipple, fussing while working), and many babies never need to move up at all.
Is paced bottle feeding only for breastfed babies?
No. Formula-fed babies get the same benefits: fewer gulping/choking episodes, less spit-up from overfilling, and fuller-fullness signaling. The 15–20 minute guidance comes from breastfeeding support 1, but the mechanics help every bottle-fed baby.
My baby chokes even on the slowest nipple. Now what?
Try a different brand’s slow nipple (flows vary widely), double-check the bottle assembly and venting, keep baby fully upright, and pause often. If choking persists across systems, call the pediatrician — recurrent choking despite slow flow can signal a swallowing-coordination problem needing assessment 5.
The short version: 5 minutes is the bottle telling on itself, not your baby asking for more. Slow the nipple, pace the feed toward 15–20 minutes, read the cues after the burp break — and size the bottle up only when a calm, slow feed still ends hungry. Log a few feeds the same way you log everything else, and the pattern will show itself within days.
Disclaimer: This article is for informational purposes only and does not constitute medical advice. Every baby is different. Always consult your pediatrician with questions about your baby’s feeding, growth, or health.
Footnotes
-
La Leche League South Africa, “Bottles” (hold the bottle horizontal — “paced bottle feeding” — feed should take about 15–20 minutes, mimicking the breast). Source ↩ ↩2 ↩3 ↩4 ↩5
-
Breastfeedo, “Bottle Feeding a Breastfed Baby: Paced Feeding, Timing, and Avoiding Flow Preference” (paced feed usually around 10–20 minutes, similar effort to a breastfeed; fast bottles risk flow preference). Source ↩ ↩2 ↩3
-
Nationwide Children’s Hospital, “Choosing a Bottle Flow Rate,” Helping Hands HH-IV-244 (follow baby’s pace, not package ages; too-fast signs: gulping, choking, hard swallowing, coughing, increased drooling, refusing; too-slow signs: longer feeds, fast sucking with few swallows, collapsing nipple, fussiness). Source ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11
-
Dr. Brown’s Medical, “Parent/Caregiver Nipple Flow Guidelines” (too-fast signs include gulping, coughing, choking, bottle refusal, falling asleep at the start). Source ↩ ↩2 ↩3 ↩4
-
Brigham and Women’s Hospital, Pediatric Newborn Medicine, “Feeding Strategies” appendix (struggling suck-swallow-breathe coordination means milk flow is too fast for the infant). Source ↩ ↩2 ↩3
-
CDC, “Signs Your Child Is Hungry or Full,” reviewed Mar. 11, 2026 (birth–5 months hunger: hands to mouth, turning toward breast/bottle, puckering/smacking/licking lips, clenched hands; full: closing mouth, turning away, relaxing hands; crying is a late hunger sign). Source ↩ ↩2 ↩3 ↩4
-
CDC, “About Feeding From a Bottle,” reviewed Mar. 11, 2026 (angle the bottle so milk comes only when baby sucks; let baby take breaks; stop on fullness cues even if bottle not empty; don’t force finishing; don’t prop the bottle — choking, ear infection, tooth decay, overfeeding risks). Source ↩ ↩2 ↩3 ↩4
-
Pados BF et al., “Milk flow rates from bottle nipples used after hospital discharge,” MCN Am J Matern Child Nurs 2016;41(4):237–243 (26 nipple types across 15 brands: 1.68–85.34 mL/min; “Slow/Newborn/0–3 mo” labels spanned 1.68–15.12 mL/min; 9/26 types had >20% within-type variability; label not a reliable flow guide). Source ↩
-
UNICEF UK Baby Friendly Initiative, “Infant formula and responsive bottle feeding” (feed on hunger cues — head movement, mouth opening, sucking fingers; crying is the last sign, feed before crying). Source ↩
Keep reading